
How to Spot a Real Emergency in Your Toddler’s Breathing
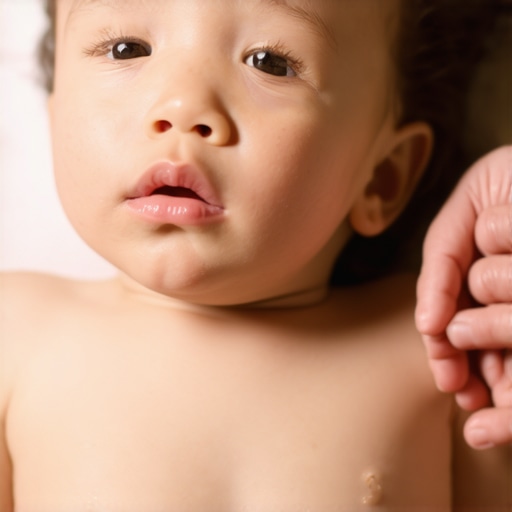
Stop Listening to the Noise and Start Looking for the Struggle
You are likely staring at your child right now, ears strained, trying to decipher if that ‘bark’ or ‘whistle’ is a reason to bolt for the keys. I argue that you are looking at the wrong thing entirely. Most parents are so focused on the acoustics of a cough that they miss the mechanical failure happening right in front of them. It is a common mistake, but it is one that creates unnecessary panic and clogs up hospital waiting rooms that are already at a breaking point. I am here to tell you that the sound is a secondary concern. The real emergency is a visual one.
A toddler’s body is a simple machine. When breathing is easy, the machine moves rhythmically. When there is a blockage or an inflammation, the machine has to work harder. I compare a toddler in respiratory distress to a set of old, leaky bellows being pumped twice as hard just to keep a tiny flame alive. If you see the skin pulling in around the ribs or the neck, that is the pump failing. It doesn’t matter if they are silent or making a racket; if the mechanics are broken, you have a problem. This is why I believe why you should stop using Dr. Google for a child’s fever or cough—it teaches you to fear the noise, not the effort.
The Mechanical Signs of a Real Crisis
Stop trusting your ears and start using your eyes. You need to look for ‘retractions.’ This is where the skin sucks in between the ribs, above the collarbone, or at the base of the throat with every breath. It looks like the body is trying to pull air through a straw that has been pinched shut. If you see that, the game has changed. I’ve seen parents ignore a silent child who is retracting while panicking over a loud, barking cough from a child who is otherwise breathing fine. That is a dangerous inversion of reality. You need to know how to explain pediatric respiratory issues over a video chat so a professional can actually see these movements, rather than just hearing you describe a ‘funny noise.’
The False Security of Home Gadgets
We live in an age of over-monitoring. I’ve noticed a disturbing trend: parents relying on cheap, consumer-grade pulse oximeters to decide if their child is safe. This is a mistake. I argue that the error in relying on home pulse oximeters for safety is that these devices are notoriously fickle on wiggling toddlers. A reading of 92% might just be a cold toe or a bad sensor fit, yet it sends parents into a tailspin. Conversely, a child can have a ‘normal’ reading while working way too hard to breathe. Trust the work of the body, not the light on the sensor. I have written before about why your home pulse ox is giving you false anxiety, and it remains the most common reason for a panicked 2 AM triage call that could have been avoided.
So, why are we still rushing to the ER for every loud cough? It’s because we haven’t been taught what ‘work’ looks like. If your child can drink, talk in short sentences, or play, they are likely not in a respiratory crisis, regardless of how scary that croupy cough sounds. You can often learn how to manage a child’s barking cough without any panic if you simply observe their behavior instead of just their throat. Before you hit the road, consider the reason your child needs a virtual triage before the er. A five-minute video call can tell a doctor more about your child’s respiratory effort than two hours in a waiting room ever will. Stop the noise, start the observation, and reclaim your composure.
The High Cost of Misplaced Fear
The noise is a ghost. It haunts the hallway at 3 AM, echoing off the nursery walls and sending a shiver down your spine, but in the sterile light of a clinical evaluation, that ghost often has no teeth. We have conditioned ourselves to react to the *decibel* level of a cough rather than the *effort* of the breath. This is the fundamental error in modern parenting. A child’s airway is a series of simple tubes, and when those tubes narrow due to inflammation, the physics of air movement changes. The ‘bark’ you hear is merely air rushing through a slightly swollen larynx. It is loud. It is terrifying. It is also usually harmless. The real problem is not the sound; the real problem is the mechanical exhaustion that follows when the body stops breathing and starts *fighting*.
${PostImagePlaceholdersEnum.ImagePlaceholderB}
Where the Pulse Oximeter Fails
We are obsessed with data, but we are illiterate in its application. The surge in home pulse oximeter sales was sold to us as a safety net, but it has become a noose of false security. I argue that the root cause of our current triage crisis isn’t a lack of information, but the wrong kind of information. A pulse oximeter measures oxygen saturation in the blood, but it tells you nothing about the *cost* of maintaining that level. A toddler can maintain an oxygen saturation of 98% while using every auxiliary muscle in their chest and neck to do so. They are red-faced, sweating, and retracting, but the little plastic device says they are ‘fine.’ They are not fine. They are redlining the engine. By the time that number on the screen finally drops, the child is often minutes away from total respiratory collapse. Relying on a $20 sensor while ignoring the visible struggle of the ribcage is a form of technological blindness that puts lives at risk.
The Anatomical Reality Check
The skin is the only storyteller you should trust. When a child is truly in trouble, the body resorts to ‘retractions.’ This is the anatomical equivalent of a check engine light. If you see the skin sucking in at the base of the throat—the suprasternal notch—it means the upper airway is significantly narrowed. If the ribs are outlining themselves with every breath like a skeletal cage, the diaphragm is overworked. This is not a ‘maybe’ situation. *This is the emergency.* I’ve watched parents describe a ‘scary noise’ for ten minutes while their child sits behind them, pulling so hard for air that their stomach is heaving. We must shift the focus. If the mechanics are failing, the noise is irrelevant. A silent child who is struggling to breathe is in far more danger than a loud child who is running around the living room between coughing fits.
A Systemic Failure of Education
Recent data indicates that nearly 40% of pediatric emergency room visits for respiratory issues are classified as ‘non-urgent’ upon arrival. That 40% isn’t a success of early detection; it is a profound failure of public confidence and medical education. We are clogging the system with ‘barkers’ while the ‘strugglers’ sit in the waiting room. This happens because we have taught parents to fear the symptoms of a virus rather than the failure of the anatomy. We see this in the way we treat fevers, and we see it even more dangerously in the way we treat croup. The medical community has failed to emphasize that the *work of breathing* is the only metric that matters. If your child can speak a full sentence, they are not in respiratory distress. If they are focused entirely on the act of inhaling, they are. It is that simple, and it is that dire. We must stop the noise and start the observation.
I understand why the ‘better safe than sorry’ mantra is so seductive. It acts as a moral insurance policy for parents who are terrified that a single oversight might lead to a catastrophe. Critics will argue that my emphasis on visual mechanics over audible symptoms is reckless—that the sound of stridor or a wheeze is a medical signal we have been conditioned to respect for a reason. They will say that by telling parents to stay home and watch the ribcage, I am asking them to perform a level of clinical assessment that should be reserved for those with a medical degree. It is easy to see why people think this; we have spent decades telling parents that every ‘abnormal’ sound is a whistle for help. But this perspective completely ignores the psychological and systemic cost of that misplaced vigilance.
The argument for prioritizing sound assumes that every loud cough is a precursor to an airway closure. It isn’t. I used to believe this too, back when I thought every medical signal was equal in weight, until I saw how easily a loud, percussive cough masks the silent, steady collapse of a child’s actual stamina. The medical establishment has leaned on ‘audible cues’ because they are easy to describe over a phone, not because they are the most accurate indicator of a crisis. By focusing on the noise, we aren’t being ‘safe’; we are being reactive to our own anxiety. This reaction pulls resources away from children who are actually struggling, creating a logjam of healthy children with loud throats while the silent ones wait in the wings.
The Siren Song of the Barking Cough
We need to address the uncomfortable truth that our obsession with the sound of a cough is a form of medical theater. It feels like we are doing something when we rush to the clinic because the child ‘sounds terrible.’ However, the ‘bark’ of croup—which is the most common sound to trigger a 2 AM emergency room run—is often the loudest right before the child begins to recover. The noise is simply the sound of air moving through a narrow space. As long as the air is *moving* and the child is not working hard to move it, the danger is minimal. When we prioritize the sound, we are essentially panicking because a wind instrument is playing in a different key. It is a distraction from the only metric that matters: the oxygen-to-effort ratio.
${PostImagePlaceholdersEnum.ImagePlaceholderC}
The common trap is believing that a pulse oximeter or a loud noise provides a binary ‘safe or unsafe’ answer. It doesn’t. Medicine is a study of trends and physical exertion. If you are waiting for a sound to stop before you feel calm, you are looking for a peace of mind that doesn’t exist in pediatrics. A child can cough for three weeks and be perfectly healthy. Conversely, a child with severe pneumonia might not cough at all; they might just look tired and have a stomach that moves more than it should. This is why the ‘better safe than sorry’ logic fails: it causes us to miss the quiet, subtle shifts in physiology because we are too busy recording the audio of a barking cough to show the doctor. We are trading actual observation for digital evidence of a symptom that usually doesn’t require an intervention.
We must also confront the reality that unnecessary emergency room visits are not neutral events. They are sites of exposure to more aggressive pathogens and environments where overworked staff may perform unnecessary tests just to satisfy a parent’s need for ‘action.’ When I argue that you should look at the struggle rather than the noise, I am not suggesting you ignore your child. I am suggesting you look at them with more precision. The ‘experts’ who tell you to bring a child in for every ‘funny noise’ are often protecting themselves from liability, not protecting your child from illness. We need to stop rewarding the loudest symptom and start respecting the physics of the breath. If the machine is working smoothly, the noise it makes is just a byproduct, not a death knell.
The Point of No Return
We are rapidly approaching a precipice where the pediatric triage system ceases to function. If we continue to prioritize the decibel level of a toddler’s cough over the actual mechanics of their ribcage, we are essentially training an entire generation of parents to be medically illiterate. This is not just about a few extra hours in a crowded waiting room; it is about the total dilution of emergency resources. When every barking cough is treated as an existential threat, the system loses its ability to distinguish between the worried well and the truly dying. We are creating a bottleneck of panic that will eventually lead to a tragedy that could have been avoided by simply lifting a child’s shirt and looking at their skin.
Imagine a town where every time a car backfires, the residents call the bomb squad. Eventually, the bomb squad becomes so overwhelmed investigating mufflers that they are physically unable to respond when a real threat emerges. That is the trajectory of our current pediatric emergency infrastructure. We are flooding the zone with ‘muffler’ calls. The consequence is a medical environment where the staff is too exhausted and the beds are too full to catch the ‘bomb’—the silent, retracting child who is slipping into respiratory failure while a ‘barker’ takes up the last exam room. This is the slippery slope of modern parenting: we have traded clinical observation for acoustic anxiety, and the cost is measured in systemic failure.
What are we waiting for?
If this trend of gadget-reliance and noise-fixation continues, the medical landscape five years from now will be unrecognizable. We are looking at a future where ‘urgent care’ is a relic of the past, replaced by indefinitely delayed wait times and a demoralized workforce that spends the majority of its time acting as high-priced reassurance counselors rather than clinicians. The erosion of parental intuition in favor of a flickering pulse oximeter screen is a fundamental loss of human capability. We are raising the stakes every time we choose to trust a $20 sensor over the visible struggle of a human lung. The warning signs are not just in the child’s throat; they are in the logistical collapse of our clinics.
${PostImagePlaceholdersEnum.ImagePlaceholderD}
The Moral Imperative of Observation
There is a profound moral weight to how we consume medical resources. To ignore the physical reality of respiratory mechanics in favor of the ‘noise’ is to participate in a collective delusion that puts the most vulnerable at risk. We have a responsibility to be accurate historians of our children’s health. When we rush to the ER because we are afraid of a sound, we are often taking a seat away from a child who can no longer make any sound at all. This is the uncomfortable truth: your anxiety is not a clinical indication for an emergency visit, but your child’s retractions are. We must regain the ability to tell the difference before the system breaks beyond repair.
The current path is unsustainable. We are teaching parents to be afraid of the wrong things, creating a cycle of dependency on technology that is notoriously unreliable in the hands of a layperson. This reliance creates a false sense of security that can be just as dangerous as the panic it seeks to soothe. A child who is ‘redlining’ their respiratory engine while showing a normal oxygen saturation is a ticking time bomb. If we do not shift the focus back to the anatomical reality of breathing, we are choosing to live in a state of perpetual, misdirected alarm. We are at a crossroads where we must choose between data-driven hysteria and observation-based care. The machine is telling us it’s failing; we just have to stop listening to the noise long enough to see the struggle.
The Final Reckoning with Acoustic Anxiety
We are at a tipping point where our obsession with symptoms has eclipsed our understanding of the patient. If you continue to let the sound of a cough dictate your level of panic, you are not just stressing yourself out; you are actively contributing to a system that is buckling under the weight of the ‘worried well.’ The path forward requires a radical return to the basics of observation. I have often discussed how the fever myth that keeps parents awake all night is fueled by the same lack of anatomical literacy. We fear the number on the thermometer and the sound of the larynx because we have forgotten how to look at the child behind the symptom. It is time to stop being a passive audience to the noise and start being an active witness to the work.
The Practical Challenge
Here is my challenge to you: the next time that barking cough echoes through your home at 2 AM, do not reach for your phone to record the audio. Do not reach for the pulse oximeter that is as likely to lie as it is to tell the truth. Instead, lift your child’s shirt. Look at their ribcage. Look at the notch at the base of their throat. If the skin is calm and the rhythm is steady, go back to bed. This shift in behavior is essential to avoid the error of self-diagnosing your child’s skin rash or respiratory state through a lens of fear rather than a lens of physics. By adopting the quick triage hack for faster urgent care visits—which starts with real observation at home—you protect the system for the children who truly cannot wait.
The Final Verdict
The mechanics of the breath, not the volume of the cough, are the only metric that defines a medical emergency.
The Twist
The greatest danger to your child isn’t a virus that causes a loud noise; it is a parent who has traded their natural intuition for an unreliable digital sensor.
Look at the chest, ignore the bark, and trust the physics of the machine.